
- Physical Examination
- Surgical Examination
- Ophthalmology
- Clinical Skills
- Orthopedics
- Surgery Videos
- Laparoscopy
- Pediatrics
- Funny Videos
- Cardiothoracic Surgery
- Nursing Videos
- Plastic Surgery
- Otorhinolaryngology
- Histology and Histopathology
- Neurosurgery
- Dermatology
- Pediatric Surgery
- Urology
- Dentistry
- Oncology and Cancers
- Anatomy Videos
- Health and Fitness
- Radiology
- Anaesthesia
- Physical Therapy
- Pharmacology
- Interventional Radiology
- Cardiology
- Endocrinology
- Gynecology
- Emergency Medicine
- Psychiatry and Psychology
- Childbirth Videos
- General Medical Videos
- Nephrology
- Physiology
- Diet and Food Health
- Diabetes Mellitus
- Neurology
- Women Health
- Osteoporosis
- Gastroenterology
- Pulmonology
- Hematology
- Rheumatology
- Toxicology
- Nuclear Medicine
- Infectious Diseases
- Vascular Disease
- Reproductive Health
- Burns and Wound Healing
- Other
Top videos




The kid swallowed a coin. Just watch how professionally a doctor extracts it, while another hospital might even perform a surgery and empty the parent's...

NEET Motivational Video |Don't Give up 🔥|#neet2023#aiims
#neetmotivation
#aiims
#neet2023
#pw#dontgiveup
#dream
#mbbs
#neet2024
#doctor
#aiimsdelh#medical

Examination of the hand and the wrist

how to apply a tourniquet

a video showing how to suture a wound

A very funny song about vasectomy

A video showing the inspection of the nose

Roux-en-Y Gastric Bypass Surgery

Dr. Jawad has been performing Bariatric Surgery in Central Florida since 1984, and Laparoscopic Bariatric Surgery since 1999, having completed over 2000 Bariatric Surgical Cases safely, and with great success. Here you can watch Dr. Jawad performing a Laparoscopic Roux-En-Y Gastric Bypass surgery, with audio commentary describing the procedure.

تناسق القوام مطلب كل أنسان سواء رجل أو أمرأة ولذلك يجب تحديد معدل تراكم الدهون بالجسم و تحديد نوع تناسق القوام و كيفيته
د. محمد الروبي
استشارى جراحات التجميل بجامعة عين شمس
Insertion of a CSF shunt

Breast reduction can relieve strain from shoulder straps, neck, back, and upper arms.
It can provide an uplift to help clothes fit and look better. Traditionally, insurance companies would provide benefits for a broad range of breast sizes and gram weight of tissue to be removed from each breast. At present most insurance companies limit authorization when the doctor plans to remove less than 500gm weight per breast. Since many patients present with symptoms in a D cup to DD cup, often, the very removal of over 500 grams weight may reduce the breasts too much. This amount of reduction may not be in harmony with body shape. Newer methods of breast assembly after reduction, will tighten things using internal brassiere techniques that also compact and reduce breast volume. Therefore, a gram weight reduction of 500gms in some patients combined with internal tightening efforts, could pose an over-reduction. With the unreliability of insurance support in some cases, it is best not to look solely at gram weight in the surgical planning of breast reduction. When excess skin and weight is removed, the improved location of the breasts on the chest will give marked relief of symptoms.
Surgery takes from 2 to 5 hours and can be done as an outpatient or with a brief overnight stay. When possible, no scarring other than around the areola can be planned which follows the Brazilian and French methods (Goes and Benelli). For very large reductions, a vertical method, or T pattern approach is offered. Recovery is a few days, with special care to avoid strain for 4 to 6 weeks. Some soreness may persist for a few weeks. The breasts can appear tight, swollen, and bruised at first, but will usually settle to their near final look by 6 weeks. There may be sutures to be removed in some cases. Costs relate to the severity of the sag, and weight of the breasts.
The operation can make a stunning change in body image, relief of upper body symptoms, and offer a cosmetic lift to naturally sloping breasts.

Endoscopic Atraumatic Coronary Artery Bypass EndoACA
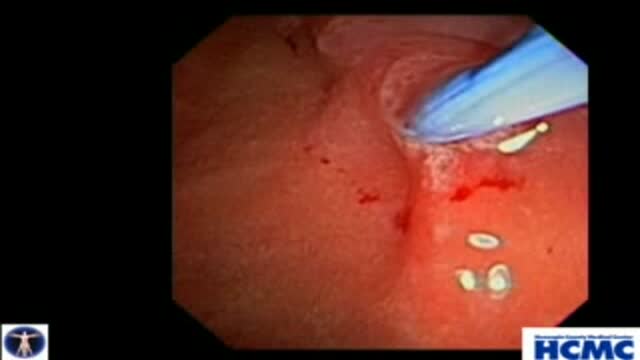
Biliary and Pancreatic Sphincterotomies for Sphincter of Oddi Dysfunction
This 43 year old woman has severe recurrent RUQ pain post cholecystectomy. Liver and pancreatic chemistries and duct size are normal, but pancreatic manometry is abnormal. The plan is to perform dual biliary and pancreatic sphincterotomy. The pancreatic duct is cannulated with a 3.9 French tip tr...iple lumen papillotome loaded with a 0.025 inch Jagwire. Contrast is injected to outline the course of the duct. The wire is passed to the tail. Notice the knuckling of the wire into the tail. This provides a safety loop, but is only safe in a small duct with use of a smaller caliber wire. Then with the wire securely in PD, papillotome is used to cannulate the bile duct. Placement of the wire in PD guarantees access for pancreatic stent placement, which is mandatory in these patients to reduce risk, it also facilitates difficult biliary cannulation. Here is the fluoroscopic view as the papillotome is passed deep into bile duct. This shows wires in the CBD and PD. Now a biliary sphincterotomy is performed, with the pancreatic guidewire in place beside the papillotome. The scope is pushed into a longer position to orient up the middle of the papilla. The sphincterotomy is done in very careful stepwise fashion to avoid perforation. Now the biliary wire is removed and the papillotome passed over the pancreatic wire for pancreatic sphincterotomy. The incision is aimed back up towards the biliary sphincterotomy to ensure the septum only is cut. Note the large pancreatic orifice. Last, a 4 French 9cm unflanged soft material pancreatic stent is placed. We always use single pigtail design to avoid inward migration of the stent. The long unflanged design allows spontaneous passage within a few weeks.
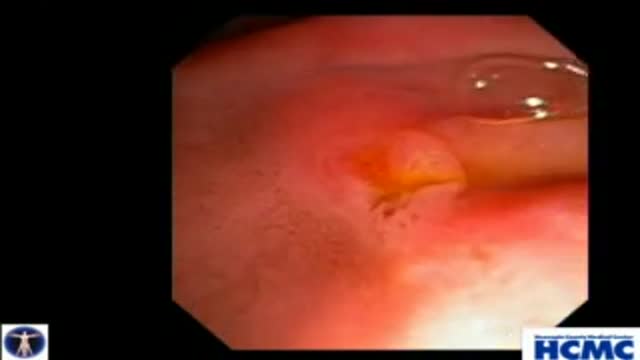
This 38 year old woman has increasingly intractable RUQ pain after cholecystectomy done one year prior. LFTs and pancreatic enzymes have been normal, and ducts are non-dilated, thus she is a Type III possible SOD patient. Initial goal is to define course of pancreatic duct for manometry. 5-4-3 Co...ntour catheter (Boston Scientific) is used to perform the pancreatogram which shows a small straight distal duct. The aspirating triple lumen manometry catheter (Wilson Cook) is used to cannulate the pancreatic duct, with continuous aspiration of fluid once the duct is entered. Careful stationed pullthrough manometry shows markedly abnormal basal pressures in both leads in the pancreatic sphincter. Plan is dual pancreatic and biliary sphincterotomy. Biliary manometry will not now change our plan therefore is omitted. Our first goal is to access the pancreatic duct so we can guarantee wire access for placement of a small caliber pancreatic stent which is critical for safety. Contrast is injected as the 0.018in Roadrunner wire (Wilson Cook) is advanced in order to outline the course of main duct. A separate biliary orifice is clearly seen, unusual in SOD patients. A soft 4Fr 3cm single inner flange pancreatic stent (Hobbs Medical) is placed. We did not want to use our typical 9cm long unflanged stent as even a 3 or 4 French stent might be traumatic to the tiny caliber of this duct out in the body of the gland. Next the bile duct is cannulated with a papillotome (Autotome 39, Boston Scientific), showing a small perhaps 6mm bile duct. Biliary sphincterotomy is performed in very careful stepwise fashion as landmarks are unclear and perforation is higher risk in small duct SOD patients. On the other hand, inadequate sphincterotomies offer limited chance of symptom relief. You can see here a patulous sphincterotomy. Next a pancreatic sphincterotomy is performed with the needle knife (Boston Scientific) over the pancreatic stent. Again this is performed cautiously due to the small size of the pancreatic duct. We are reaching along the stent and cutting the fibers deeply. This is a limited pancreatic sphincterotomy due to small pancreatic duct size, and concern for scarring of the pancreatic duct. It is important to document passage of the stent by xray or remove it endoscopically with two weeks or so. We and many other specialized centers perform dual sphincterotomies at the first ERCP in all SOD patients with abnormal pancreatic manometry and frequent or intractable symptoms based on the belief that response rates are better than for biliary sphincterotomy alone.
