
- Physical Examination
- Surgical Examination
- Ophthalmology
- Clinical Skills
- Orthopedics
- Surgery Videos
- Laparoscopy
- Pediatrics
- Funny Videos
- Cardiothoracic Surgery
- Nursing Videos
- Plastic Surgery
- Otorhinolaryngology
- Histology and Histopathology
- Neurosurgery
- Dermatology
- Pediatric Surgery
- Urology
- Dentistry
- Oncology and Cancers
- Anatomy Videos
- Health and Fitness
- Radiology
- Anaesthesia
- Physical Therapy
- Pharmacology
- Interventional Radiology
- Cardiology
- Endocrinology
- Gynecology
- Emergency Medicine
- Psychiatry and Psychology
- Childbirth Videos
- General Medical Videos
- Nephrology
- Physiology
- Diet and Food Health
- Diabetes Mellitus
- Neurology
- Women Health
- Osteoporosis
- Gastroenterology
- Pulmonology
- Hematology
- Rheumatology
- Toxicology
- Nuclear Medicine
- Infectious Diseases
- Vascular Disease
- Reproductive Health
- Burns and Wound Healing
- Kidney Zone Podcast
- Other
Top videos


http://www.landging.com/plane-animation.html
420 seconds 3d plane animation, designed for Expo 2010 Shanghai Aviation Pavilion.
Bradyarrythmias
Carpal tunnel release (part 1). Skin incision and retraction. Procedure performed by Deepak Kapila, MD, Broward Health, Fort Lauderdale, FL. Courtesy of BroadcastMed (http://ortho.broadcastmed.com/....4229/videos/carpal-t
There are hundreds more procedural videos as well as news, features, resources and references on Medscape.com. Join today for free.

This video: Pancreatic cancer begins in the tissues of your pancreas — an organ in your abdomen that lies horizontally behind the lower part of your stomach. Your pancreas secretes enzymes that aid digestion and hormones that help regulate the metabolism of sugars. Pancreatic cancer often has a poor prognosis, even when diagnosed early. Pancreatic cancer typically spreads rapidly and is seldom detected in its early stages, which is a major reason why it's a leading cause of cancer death. Signs and symptoms may not appear until pancreatic cancer is quite advanced and complete surgical removal isn't possible.

demonstrates how the Epley maneuver is performed to treat POSTERIOR canal BPPV affecting the right ear. Animation showing what is going on within the inner ear is also shown in the 2nd half of the video.
Pyogenic granuloma (lobular capillary hemangioma[1] ) is a relatively common benign vascular lesion of the skin and mucosa whose exact cause is unknown. Also see the Medscape Reference article Oral Pyogenic Granuloma. Pyogenic granulomas are misnamed; they are neither infectious nor granulomatous. The lesion usually occurs in children and young adults as a solitary, glistening red papule or nodule that is prone to bleeding and ulceration. Pyogenic granulomas typically evolve rapidly over a period of a few weeks, most often on the head, neck, extremities, and upper trunk. Pyogenic granuloma often arises in pregnancy (or rarely with oral contraceptive usage), particularly on the gingiva or elsewhere in the oral mucosa, and then is termed the "pregnancy tumor." Other pyogenic granuloma variants that have been well documented include the disseminated, subcutaneous, intravenous, and medication-induced (for example, retinoid, antiretroviral, and oncologic agent) subtypes. Removal of pyogenic granuloma is indicated to alleviate any bleeding, discomfort, cosmetic distress, and diagnostic uncertainty. A number of malignant tumors may clinically mimic pyogenic granuloma, making histopathologic confirmation important if the presentation is atypical. Aside from cutaneous and oral lesions, pyogenic granuloma has been reported throughout the gastrointestinal tract and upper airway, at various ocular locations, the central nervous system, the bladder, and the internal vasculature. This article discusses only cutaneous and oral involvement.

Laparoscopic Gastric Bypass Surgery

University Hospitals Neurological Institute will host a live webcast to demonstrate the removal of a brain tumor that doctors believe is causing epileptic seizures in a middle-aged man.
An MRI showed what appears to be a glioma (tumor) near a part of the brain that controls muscle movement, called the motor strip. Studies have shown that complete removal can cure the seizures and improve quality of life and survival, but this is difficult to do with conventional technology without harming the surrounding normal brain because it's difficult to determine where tumor ends and normal brain begins.
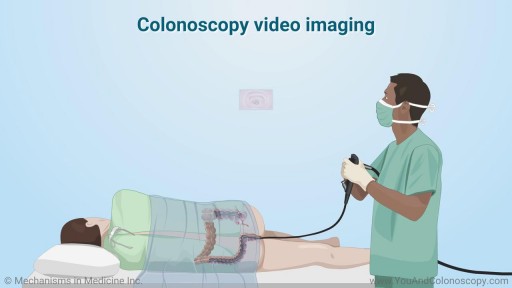
A colonoscope is the special tool used to perform a colonoscopy. It is a thin, flexible, tubular ‘telescope’ with a light and video camera that your doctor carefully guides through your colon in order to see and determine the health of your colon. Watch this animation to learn about the features of the colonoscope, how the colonoscopy procedure is performed and how polyps are removed, and the follow-up care you and your doctor should talk about after your procedure.
Liver transplantation is surgery to remove a diseased or injured liver and replace it with a healthy whole liver or a segment of a liver from another person, called a donor. People with either acute or chronic liver failure may need a liver transplant to survive.
Histology of Dorsal Root Ganglion
Intracranial pressure (ICP) is the pressure inside the skull and thus in the brain tissue and cerebrospinal fluid (CSF). ICP is measured in millimeters of mercury (mmHg) and, at rest, is normally 7–15 mmHg for a supine adult.


Clinical Review First aid and treatment of minor burns BMJ 2004; 328 doi: https://doi.org/10.1136/bmj.328.7454.1487 (Published 17 June 2004) Cite this as: BMJ 2004;328:1487 Article Related content Metrics Responses Jackie Hudspith, clinical nurse lead, Sukh Rayatt, specialist registrar, plastic and reconstructive surgery Author affiliations Introduction Some 250 000 burns occur annually in the United Kingdom. About 90% of these are minor and can be safely managed in primary care. Most of these will heal regardless of treatment, but the initial care can have a considerable influence on the cosmetic outcome. All burns should be assessed by taking an adequate history and examination.
Electronystagmography (ENG) is a diagnostic test to record involuntary movements of the eye caused by a condition known as nystagmus. It can also be used to diagnose the cause of vertigo, dizziness or balance dysfunction by testing the vestibular system.
Sebaceous Cyst, Hematoma and Growth Removal
A sneeze, or sternutation, is a semi-autonomous, convulsive expulsion of air from the lungs through the nose and mouth, usually caused by foreign particles irritating the nasal mucosa
Hematoma Removal! Surgery, Blood, Popping
Whereas it is true that no operation has been profoundly affected by the advent of laparoscopy than cholecystectomy has, it is equally true that no procedure has been more instrumental in ushering in the laparoscopic age than laparoscopic cholecystectomy has. Laparoscopic cholecystectomy has rapidly become the procedure of choice for routine gallbladder removal and is currently the most commonly performed major abdominal procedure in Western countries.[1] A National Institutes of Health consensus statement in 1992 stated that laparoscopic cholecystectomy provides a safe and effective treatment for most patients with symptomatic gallstones and has become the treatment of choice for many patients.[2] This procedure has more or less ended attempts at noninvasive management of gallstones. The initial driving force behind the rapid development of laparoscopic cholecystectomy was patient demand. Prospective randomized trials were late and largely irrelevant because advantages were clear. Hence, laparoscopic cholecystectomy was introduced and gained acceptance not through organized and carefully conceived clinical trials but through acclamation. Laparoscopic cholecystectomy decreases postoperative pain, decreases the need for postoperative analgesia, shortens the hospital stay from 1 week to less than 24 hours, and returns the patient to full activity within 1 week (compared with 1 month after open cholecystectomy).[3, 4] Laparoscopic cholecystectomy also provides improved cosmesis and improved patient satisfaction as compared with open cholecystectomy. Although direct operating room and recovery room costs are higher for laparoscopic cholecystectomy, the shortened length of hospital stay leads to a net savings. More rapid return to normal activity may lead to indirect cost savings.[5] Not all such studies have demonstrated a cost savings, however. In fact, with the higher rate of cholecystectomy in the laparoscopic era, the costs in the United States of treating gallstone disease may actually have increased. Trials have shown that laparoscopic cholecystectomy patients in outpatient settings and those in inpatient settings recover equally well, indicating that a greater proportion of patients should be offered the outpatient modality
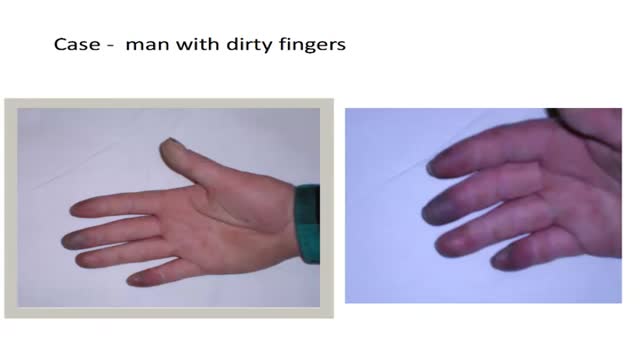
How to diagnose digital ulceration in out patient clinic.part III
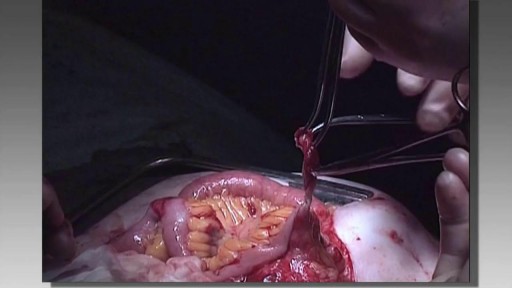
Totally Stapled Bowel Resection and Anastomosis