
- Physical Examination
- Surgical Examination
- Ophthalmology
- Clinical Skills
- Orthopedics
- Surgery Videos
- Laparoscopy
- Pediatrics
- Funny Videos
- Cardiothoracic Surgery
- Nursing Videos
- Plastic Surgery
- Otorhinolaryngology
- Histology and Histopathology
- Neurosurgery
- Dermatology
- Pediatric Surgery
- Urology
- Dentistry
- Oncology and Cancers
- Anatomy Videos
- Health and Fitness
- Radiology
- Anaesthesia
- Physical Therapy
- Pharmacology
- Interventional Radiology
- Cardiology
- Endocrinology
- Gynecology
- Emergency Medicine
- Psychiatry and Psychology
- Childbirth Videos
- General Medical Videos
- Nephrology
- Physiology
- Diet and Food Health
- Diabetes Mellitus
- Neurology
- Women Health
- Osteoporosis
- Gastroenterology
- Pulmonology
- Hematology
- Rheumatology
- Toxicology
- Nuclear Medicine
- Infectious Diseases
- Vascular Disease
- Reproductive Health
- Burns and Wound Healing
- Kidney Zone Podcast
- Other

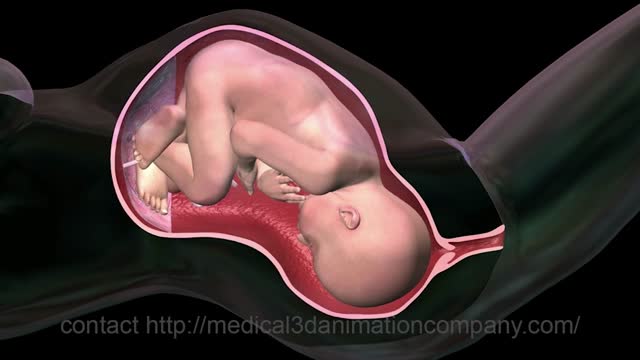









Full Obstetric Examination and Normal Delivery

Full Obstetric Examination and Normal Delivery medical video
This video in 30 seconds
A long obstetric teaching film works through abdominal examination of a pregnant woman, including lie, presentation, position and fetal heart sounds. It then shows a normal delivery including episiotomy and its repair, discussion of obstetric forceps, and pelvimetry measuring the pelvis.
Key points
- The instructor demonstrates abdominal examination for lie, presentation and position
- Fetal heart sounds are listened for by different methods
- The mechanism and stages of a normal delivery are shown
- Episiotomy and its layered repair are demonstrated
- Obstetric forceps and pelvimetry are discussed in detail
Chapters
- 0:10 — Introduction to obstetric procedures
- 2:55 — Abdominal examination and presentation
- 14:19 — Listening to the fetal heart
- 22:23 — Mechanism of normal delivery
- 29:20 — Delivery of the placenta
- 34:24 — Pelvimetry and bony pelvis
- 47:13 — Obstetric forceps design and use
- 1:05:20 — Episiotomy during assisted delivery
Video Transcript
A long obstetric teaching film for students, presented by an Egyptian doctor. It works through the abdominal examination of a pregnant woman — lie, presentation, position and fetal heart sounds — then a normal delivery including episiotomy and its layered repair, and finishes with pelvimetry, the measuring of the pelvis with calipers and fingers. It is the full-length companion to the 'Part 2' obstetrics tape elsewhere in this batch.
Read the full transcript
For the sake of science.
For the sake of medicine. For the sake of my young sisters and brothers. I have the honor to announce the birth of a new project. Hello, colleagues. Welcome on this film which describes the obstetric procedures and operations. On this film you shall see what is going on at busy obstetric unit. The more you play back this tape, the more you see the obstetric procedures and the more you learn. So when the day comes that you will find yourself confronted with any of these obstetric procedures. You will know where you are and you will know exactly what you are going to do and to manage these cases.
We are going to start by abdominal examination of the pregnant woman. Of course we assume that you have already examined the patient generally, has taken her blood pressure, has examined her chest, her heart, have looked for a deal of the lower limbs and now you are coming to examine her abdomen. By abdominal examination you are going to detect the lie, presentation and position of the fetus. You are going to detect the attitude and level of the presenting part and its relationship to the pelvis. You are going to detect the presence and the characters of the fetal heart sounds.
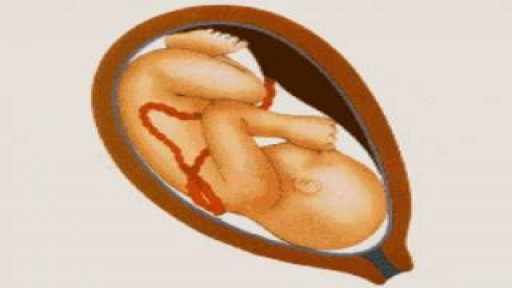
Put us together, how we examine the pregnant patient. First we can detect whether the fetus is lying longitudinally, transversely inside the abdomen. Second we can detect as well the presentation, whether the fetus is presenting by its head or it is presenting by its preach. Thirdly we can also detect the position of the fetus. When the fetus is presenting by its head we have four positions. The first position what we call left occipital anterior. That means that the back of the fetus as you can see on this picture is on the left side of the mother.
And so as the back is on the left the occiput again is on the left because the occiput is on the same direction as the back. The second position is when the back is on the right side but still anterior. That's why we say right occipital anterior. Again we still refer the occiput on the direction of the back. The third position is the right occipital posterior. Now the back is turned as we can see on this picture is turned to the posterior side or towards the back of the mother.
But it's still on the right side. That's why we call it right occipital posterior. The fourth and last position in the Catholic presentation is the left occipital posterior. That means the back is on the posterior side and is on the left side of the mother. Left occipital posterior. When the baby is presenting the birth of its breach we refer the position to the sacrum. So we have similar positions. Left sacro anterior. Right sacro anterior. Right sacro posterior. And left sacro posterior. Now we come to examine the fetus.
The examination of the fetus is started by doing the fundal palpation or fundal grip. And with the two hands laid flat upon the fundus of the uterus while you are facing the patient, you should note first the level of the fundus. This will give you an assessment to the period of gestation. Second, you feel the part occupying the fundus which more commonly is a breach and will be felt as a large firm regular body continuous with the trunk of the fetus and moving with it. If the head occupies the fundus it would be felt as hard, round and ballottable when it would be in this position.
Then we come to the lateral grip. By the lateral grip we want to estimate and to know where is the back of the fetus. And the back is a smooth rounded surface here. Now I can feel it on the left side of the uterus. And on the other side I can feel knobs or irregularities which confirm the limbs of the fetus here. The third grip we come to the first pelvic grip. And first pelvic grip is by inserting my hands down here and trying to push and approximate my fingers towards each other.
And if the presenting part is engaged that means that the main diameter of the presenting part has passed through the pelvic inlet, so my fingers will not approximate to each other. And the presenting part is intervening between my fingers from the left fingers and my right fingers. And this is the first pelvic grip. And it is more important when the presenting part is engaged in the pelvic cavity. Now when we come to the second pelvic grip and there is my hand here on the bubis and then trying to touch the presenting part between the stretched finger and the thumb here.
It is useful when the presenting part is high. And now I can feel the head as hard, round and then ballottable which is high because it is high. So it ballots between my finger and the thumb here. This is the fetal head. By this we can summarize, we can say that this fetus is a longitudinal lie, is a catholic presentation and it is left occipital anterior position and as the head is not engaged. This is the conventional fetal stethoscope which is called the pinnald stethoscope which has got a wide mouth here and an arrow opening which fits on the ear.
It do come either in metal or in plastic. And this is commonly used to listen for the fetal heart sounds. This is the commonly used sonic aid which is used for listening to the fetal heart sound. As we can see here, so this snap is switched on and off. This is a battery indicator and then has got a drawer here so we can get its attachment. This is a plug cord and the plug to be connected to the main, whenever you want it to be charged. This knob is fixed here and this is connected to a transducer.
This is a KY jelly which is used to print the abdomen of the patient so it would allow the easy transmission of sound. So we open here and then we can see how the transducer is so sensitive. We shall see now in a minute how it is used clinically. This is another type of fetal sonic aid which is rather small and portable. It consists of the sonic aid itself just like a small cylinder with a loud speaker box and its attachments. Now if we can attach this cord to the loud speaker and this one here, then we open and then if we use it we just press on the button.
We use on the button so the transducer here will be put on the abdomen and then we transmit the sound. When we release the button so there will be no sound transmitted. By using the loudspeaker the patient himself can listen to the beats of her own fetus. If the doctor just wants to listen to the fetal heart so we can fix the other attachment here and then will be used as ordinary stethoscope. Just fixing this to the ear. Now we are going to ascultate the fetal heart.
This is the penile stethoscope which we have just seen and have a wide mouth end. This patient, an oral patient, we diagnose that the fetus lying longitudinally with its back on the left side. So the area which we are expecting is on the back, on the scapula and that would be the scapula of the baby. And then the area where we expect to listen to the fetal heart in this case would be here. And if we put the penile stethoscope and then trying to listen now I can hear the fetal heart regular and quite audible.
In left occipital anterior position the fetal heart is best heard towards the left iliac fossa as marked on this picture. In right occipital anterior it is towards the right iliac fossa. In posterior positions the area is further lateral towards the flanks as we can see. When the back of the fetus is extended in posterior positions this will bring its chest forwards against the anterior uterine wall. And the fetal heart is best heard towards the midline, an area which is directly over the fetal heart. In bridge positions the area is further upwards above the umbilical plane.
In left occipital anterior it is on the left and in right occipital anterior it is on the right. This is another model of the sonic aid which is different than we have seen. And now we are trying to listen to the fetal heart with the sonic aid. We have to wet the abdomen of the patient with sound transmitting substance like k-wajjali. Sometimes we use alcohol and as well as we are going to mob the transducer. And then placing it here, here we can hear. To summarize we can make a complete diagnosis of presentation and the position of the fetus from abdominal examination alone.
The head in the pelvic brim that is kefalic presentation. The head is flexed that is vertex presentation. The head is fixed and the greater part of it has passed the pelvic inlet that means the head is engaged. The back is already felt anterior that is either on the left side it would be first position or it on the right side and it would be the second position. Or the back cannot be felt but the limbs are easily felt that means posterior positions. Now we shall see together what is meant by pelvic scoring.
During the last few weeks of pregnancy you will notice certain changes in the cervix as well as changes in the descent of the presenting part. These changes are described and recorded numerically. The changes in the cervix include dilatation, effacement, consistency and position. The changes in the presenting part is referred as station. Careful evaluation of pelvic score has been made by pajajali examination of the cervix and the presenting part. Analysis of these observations indicates a direct relationship between the pelvic scoring and the subsequent date of spontaneous onset of labor.
As regards cervical dilatation when the cervix is dilated less or up to 1 cm as 0 pelvic score for dilatation is made. When the cervix dilated 1-2 cm it scores 1. When the cervix is dilated 3-4 cm it scores 2. A diameter of 5-6 cm of the cervix or more may be reached before the onset of labor, a pelvic score 3 is recorded. As regards effacement. Effacement of the cervix is the second factor to be assessed when making a pelvic scoring. When the cervix is effaced about 30% as your score is made.
The 40-50% effaced has occurred as score 1 is made. Between 60-70% the score becomes 2. Any cervix is effaced more than 80% will score as 3. As regards station. Is the relationship between the foremost area of the presenting part and the level of the escalospine. For the papers of pelvic scoring it is estimated by the oxidation in cm above or below the plane of the escalospine. A head fell 3 cm above the escalospine scores 0. 2 cm above scores 1. As it descends engagement occurs and scores 2.
Further descent scores as 3. As regards consistency of the cervix is next estimated. Firm cervix is recorded as 0. As progressive softening occurs is recorded 1 or 2. As regards the position in which the cervix is placed in relation to the axis of the birth canal completes the 5 factors of pelvic scoring. The posterior position gives 0 scoring. When the cervix is in mid position it is 1 and the posterior position scores 2. As pregnancy proceeds they scores in various columns change and the total pelvic score rises.
As the score is 1 is recorded the average time lapse before the patient goes into labor is 20 days. When the score goes up to 5 the time lapse is 9 days. Score 9 or more almost all patients will be delivered within one week. Normal delivery is conducted. I just want to emphasize that delivery of the baby goes into 3 stages. The first stage is preparatory where the lower segment of uterus is formed. The cervix starts to dilate as well as starts to thin out the condition we call it a facement or taking up of the cervix.
This stage ends when the cervix has completely disappeared and the birth canal becomes one tube. Comprises the uterus, the cervix as well as the vagina. Then the second stage starts which composes the delivery of the baby. The most difficult part in delivery of the baby is the head. Once it is delivered in majority of cases the body will follow straight away. The fetal head during its delivery goes through consequent movements during its labor. First flexion if it hasn't been already flexed then internal rotation. Then it will be delivered by extension.
Once the head is delivered out then it returns its original position. A process we mention restitution. Then when the shoulders come to the pelvic floor they rotate. And this will be reflected to the head as external rotation. All these movements are accompanied by descent of the head. Let's see together how normal delivery is conducted. As the fetal head begins to show the situation is that the head is well flexed and ready to pass out the pubic symphysis internal rotation has taken place. From below the fetal head lies with the surgical suture in the antoposture diameter of the pelvic outlet and is occipital anterior.
Then we swab the vulva and then here we assist in normal delivery. The head should remain well flexed to allow the smallest diameter, the suboccipital brigmatic diameter to pass through the entroitus. As the head continues to advance it passes under the symphysis pubis to the position of crowning when the widest diameter is at the entroitus. Now extension of the head occurs to sweep the face over the perineum and the head is completely delivered. The shoulders now lie in the right oblique diameter and once the head rotates in the movement known as restitution
the shoulder reaches the pelvic floor and rotates into the antoposture diameter carrying the head with it to complete movement of external rotation. Here it is as we can see. This is the patient and we are conducting her normal delivery. We are going now to do infiltration at the site of the episiotomy with the liginokane 1% as we can see. We inserted the needle at the site of the episiotomy with the scissors here, the episiotomy away from the midline. As we can see will be extended to bring the face over the perineum.
At the same time we are supporting the perineum with the left hand slowly now the face is out as we can see. Then we swap the baby's eyes and now we assist the process of restitution. Here you can see the head has restituted itself in the left occipital anterior position. Restitution now occurs followed by external rotation of the occiput. As the shoulder is now in a position we see the anterior shoulder lying under the synopsis and the posterior shoulder lying against the perineum. Gentle interaction on the head towards the anus will assist the anterior shoulder to pass under the synopsis.
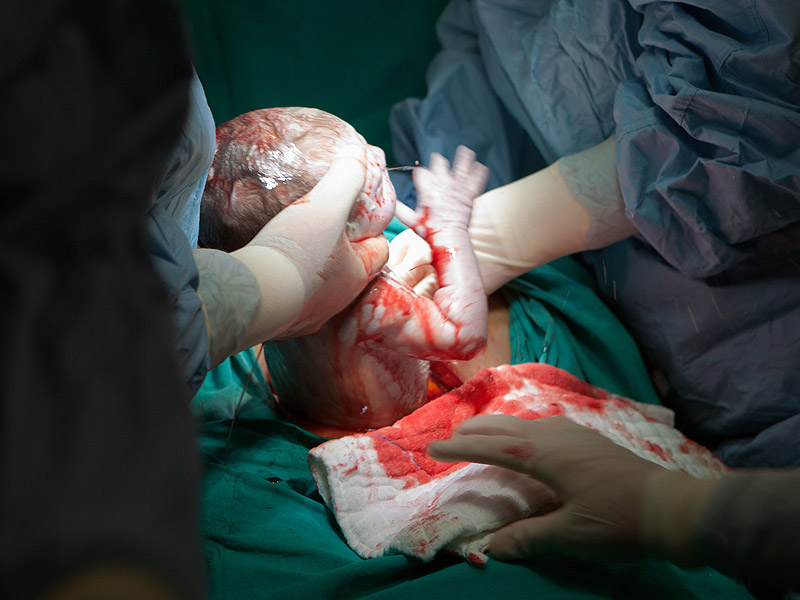
Then gentle interaction anteriorly will bring the posterior shoulder over the perineum. For the rest of the baby is delivered there will be lateral flexion of the trunk over the mother's abdomen continuing the curve of the birth canal. Here on the patient again we are lifting the baby to deliver the posterior shoulder. Here then the rest of the baby here it is. In whereby a mucus circle or a catheter we suck the nasopharynx of the baby and our assistant is tying its umbilical cord. Now the baby has been delivered. The third stage of labor is commenced and this includes the delivery of the after birth or the placenta.
Immediately following the birth of the baby the uterus contracts to the level of the umbilicus and a bit of placenta is shielded off. In this process the blood sinuses are torn and bleeding occurs behind the placenta. Subsequent uterine contractions will push the placenta in the lower segment then into the vagina with the retracting uterus on top. Putting the numberings behind it and determining them inside out. The crisscross fibers of the uterine muscles which surround the blood sinuses retract as in third stage proceeds and close up the sinuses.
This is described as shield's mechanism of spontaneous delivery of the placenta. Now this is the placenta showing here by spontaneous delivery and then by gentle traction on the cord that we can see the placenta is coming out. A gentle fundal pressure will assist the delivery of the placenta. Once the placenta is out then we'll hold it and then twisting the membranes the suck of membranes like that so it will come in one go. When the placenta is out so we have to inspect the placenta and this is the suck.
We invent the amniotic suck and then we see the placenta with the cotididons is complete. There's nothing missing. If the placenta is retained for over half an hour showing the no signs of the spontaneous separation, interference should be performed and is indicated. First you should capitalize the patient and evacuate the urinary bladder because in the majority of cases where the placenta is held a full urinary bladder. Then proceed to a method called controlled cord traction or what's called modified brand anguars technique. Let us see together how it is done.
This is a delay in the delivery of the placenta and we are going to do the brand anguars technique to separate the placenta. We have already catheterized the patient and now I'm putting the ulnar surface of the hand over the patient's supra-pure curation and with my right hand I am holding the stump of the umbilical cord. In the so called controlled cord traction instead of putting the ulnar surface of the hand on the patient's abdomen, one will put the stretched finger and the thumb. It's more or less the same technique.
Then by making a traction with my right hand accompanied with counter traction of my left hand which is put on the patient's abdomen. Now we can see together some trickling of blood through the vagina. This is a sign of the placenta separation as well as of course elongation of the cord. The placenta is shown and is coming slowly. You still maintain the traction and counter traction and then the placenta is out with the membranes dragging the membranes behind it. Then you open the amniotic syrup and you should always get used to examine the placenta after each delivery.
The placenta is complete. Here it is. Most of the instrumental obstetric delivers, however forksips or vintuels, could be done under bilateral, bodendal nerve block as well as perineal infiltration without resorting to general anesthesia. Let us see how the bodendal nerve is done. This is a diagram showing the back of the sacrum as well as the crotial region, sacrospinus ligament, sacrotubus ligament and here is the internal bodendal nerve as it crosses on the tip of the ischial spine passing from the greater to the lesser sciatic foramina. Next to it we can see together the bodendal artery as well as the nerve to obturator internus muscle.
This is the syringe and needle used in the technique and we can use the spinal needle which has got a special metal guard. If we can't find this guard, we can use a piece of plastic guard which we take it from the introducer of ad intrauterine device as we will see together when we come and see the technique with me. This is just the bony pelvis and we can see here the ischial spine and the bodendal nerve is just passing on the tip of the ischial spine.
This is the needle we use and you can notice that I have put a plastic guard on the needle and leaving only about half centimeter at its tip which this would be injected. The idea is to hit the internal bodendal nerve near the ischial spine and then we can inject the anaesthetic substance. Now we are going to demonstrate how we are doing the bodendal nerve block and perineal infiltration. Here is the patient's label and then we are going to take this is ligino grade 1% and we are going to fill the syringe.
This is the longest spinal needle which we can use and then we have two methods for attacking the bodendal nerve. Either from outside through the perineum or from inside through the vaginal skin. The external method is just putting my fingers in the vagina, directing my index finger and the middle finger toward the ischial spine. Here I can feel and then inserting the needle through the perineum, directing towards my finger here through the ischial rectal force until it reaches the ischial spine. Now I can feel the tip of the needle inside and then we can inject 10cc of the ligino cane on this side.
Again we are filling the syringe, another 10cc and then we will repeat the same procedure on the other side by my right index and finger directed toward the ischial spine. Then we push the tip of the needle through the ischial rectal force directing its tip towards my fingers inside to the ischial spine. Then we make sure that the needle is not hitting a vein and then we start pushing the anaesthetic ligino cane 1% the 10cc as we can see here. Now this is the internal method and we are using now a plastic guard. We insert it on the needle and only about 1cm at the tip of the needle is shown.
And then we shall see together the internal method of a botanical nerve block which is commonly used. This is just the diagram which we saw to remind you of the anatomy of the botanical nerve. In this patient we are going to do the botanical nerve block. Here is the syringe and the spider needle. Then we insert the guard on the needle and then we hold the guard on the tip of the index finger and then we insert the index finger here taking the guard together directed towards the spine of the ischium.
And then we push the tip of the needle behind the ischial spine and then we make sure that it is not in a blood vessel and then injecting the ligino cane. The substance will be injected around the botanical nerve and blocking it. Here it is. Now the same procedure will be repeated on the opposite side. Again we take the tip of the guard on the index finger while the tip of the needle is withdrawn inside the guard. Direct it towards the ischial spine and then again you push the anaesthetic substance.
This is the internal method which is commonly used and for any operative delivery you see. This is associated with infiltration of the perineum so it would complete anaesthetizing the whole area of the perineum. Whenever you find that the perineum is tight and narrow particularly in primary gravity and you have the feel of perineal laceration go ahead and do a pisiotomy. A pisiotomy is also done in instrumental delivery when you apply the mid-cavity forksips or caitland forksips. Also it is indicated when you conduct a premature delivery because by a pisiotomy you avoid the tight compression of the perineum on the delicate feet and head of the premature baby.
Let us see together how this pisiotomy is done and sutured. We have already seen at the beginning of this tape how it is done during the normal delivery. Now we shall see how we are going to stitch it. Now here with the chromic number one or number zero cut cut we take the apex. Our first stitch is at the apex of the vaginal skin as we can see. Then a continuous through and through stitch taking the vaginal mucosa. Here we are. Then we take a stitch at the foreshad here where is the remnant of the hymen.
We adjust the foreshad together and then another stitch between the foreshad and the mucocoutinous junction. Then our last stitch at the mucocoutinous junction here. Then we tie. This is our first layer in stitching the pisiotomy. We stitch it here and then we come to stitch the perineal muscles. That is the perineal muscles. Then we put about two or three interrupted figure of eight hemostatic sutures. Using number one chromic cut cut here and then we will go again to make a figure of eight. Here it is through the perineal muscles.
Another stitch figure of eight because figure of eight sutures are hemostatic. And by this we can prevent the incidence of hematoma in the SQO vector fossa as well as infection. Then our last layer is the skin by interrupted sutures and then we can use either plain or chromic cut cut. But here we change the needle to a cutting needle instead of the round one which we have been using on the vagina and in the muscle. We cut the thread too short, very short as possible. So it wouldn't hit the patient later on and pricking the patient as this area is very sensitive.
Here very short cut edges and of course using a cut cut we do not bring the patient to take any stitches out. So the cut cut would dissolve by itself and here the skin is sutured and completed. The obstetric forksips are designed to grasp the fetal head when it is in the vagina and affected delivery by interaction without causing injury. They are the long curved, the small, wriggly forksips and the keyland forksips. This is the long curved obstetric forksips. The most famous are Neville's type and Milne-Marie type.
This is the Neville forksips. Any obstetric forksips however the long, the short or keylands consist of two arms or branches. The branches are named right and left according to the side of the maternal pelvis into which it is introduced. Each is formed of four components, the blade, the shank, the lock and the handle. The branch of this forksips is about 15 inches in length and is made of four parts. The blade, 7 inches in length, finasterated to be light and to minimize compression of the fetal head and to avoid slipping of the forksips by allowing the parietal eminence to protrude through the finestiva.
Each blade has two curves, a catholic curve and a pelvic curve. The catholic curve conforms to the shape of the fetal head and is adapted to provide a good application to the fetal head and the pelvic curve with that of the berth canal. The blades are connected to the handles by the shank which give the requisite length to the instrument. The two blades are separated by about three and a half inches allowing a fist to pass in between. At their tips, the distance is about one inch allowing two fingers to pass in between.
The shank is about two to two and a half inches in length to allow locking of the blades outside the vagina. Its lock is that of a slot or English lock. Other forksips have screw or French lock or combined or German lock. The fill is about six inches in length and either serrated to give a good grip on the hand or smooth like this forksips. This is the axis to action piece which is attached to the forksips. Here it is. It is fixed to the forksips. The value of this axis to action piece is to allow to action in the correct direction of the berth canal.
That's to say downwards and backwards and to avoid loss of force against the symphysis bupus. This will be achieved by getting these two arrows along each other during the interaction. As we can see, we bring these two arrows together during the interaction. Anyway, this technique of axis to action is largely unnecessary in present day practice in which difficult forksips delivery is avoided. As you can see here, that is the way how we pull and use the axis to action piece. As high forksips delivery is not nowadays used and what is more commonly used in present day practice
either mid forksips or low forksips. Now we come to the indication of forksips delivery. First we have the prolonged second stage. Whenever the second stage is prolonged then half to one hour. And then we have fetal indications. When there is fetal distress or if there is prolapse pulsating cord or if there is the after coming head in breach delivery or in elective placental insufficiency. Maternal indications either maternal distress or in maternal diseases as heart failure, preclinical emptiness, pneumonia, etc. When we apply the forksips we must have conditions before applying it.
What we call the conditions to be fulfilled before forksip delivery. These are fully related cervix, raptured membranes, head must be engaged there is presence of uterine contraction, the bladder should be empty there is no kefalopelvic dyspore portion, the head is in a suitable position and also an aphasia or bilateral podendone of the block as well as complete aseptic techniques. Now we are going to see together how we do a mid cavity forksips delivery. In this patient the indication for the forksip delivery is fetal distress while she is in the second stage and the cervix is fully dilated.
Now this is neville barns forksips which has got a pelvic curve and a kephalic curve and this is a way how it would be locked inside on the fetal head. This is the right blade which is held by the right hand and is applied on the right side of the patient. Now we are going to insert the left blade, we will locate the left blade which is held by the left hand and is going to be inserted on the left side of the patient. By putting the right index and middle finger inside the vagina
and then sliding the blade along the fingers between the fetal head and the vaginal wall sliding easily and smoothly until it slides and inside. The same procedure is done with the right blade and then lubricated by hebutane or by savelon and then the left fingers are now put and the blade is held by the right hand and then would be slide smoothly between the fingers and the fetal head as this would be guided here. And then when the forksips is properly applied on the fetal head it will lock easily as you can see.
If it doesn't lock easily so you have to take the forksips out, recheck the position of the fetal head and then reapply it again. I just would love to remind you that the cervix must be fully related and the bladder must be empty. Now we are going to do a small episiotomy here as you can see and then we start traction. Then you unlock every now and then you unlock the forksips. So this would relieve the pressure on the fetal head and then start traction again especially with a uterine contraction. Now here it is. See the head is coming and out
and then you would support the perineum so the episiotomy will not be extended here. Support the perineum and until you see the ox foot is being delivered or merged under the symphysis pupus then you start to lift the head here. To lift the head and that's ox foot here. And then you start to lift your hands with the forksips to deliver the baby's head in extension. I just would like to remind you with the conditions to be fulfilled in doing forksips delivery. The patient must be catheterized and the bladder should be empty.
There is no cathalopylvic disciparaportion. The head in this suitable position and is engaged. The cervix must be fully dilated. These are the main criteria before doing forksips delivery. Again to our patient the head is now delivered by extension and then we take the blades of the forksips out. Now we help the mechanism of restitution and external rotation of the head and then delivering the anterior shoulder then the posterior shoulder of the baby and this would the baby will follow. You can notice the meconium, the heavily meconium is stained like well due to the fetal distress.
Now we clamp the umbilical cord and then we cut the cord and handle the baby to abit iteration for resuscitation. We check the uterus is firmly contracted over the placenta and the anise should give metharagine at that time. And then we can test the separation of placenta by making a gentle traction on the cord and see how whether it is elongating or still fixed here. It's still fixed. We just would like to enumerate together the causes of failed forksips. We can divide these causes into maternal causes and fetal causes.
Under maternal then we can see there is contracted pelvis or contraction ring. This is definitely will cause failure of forks of delivery. If there is incomplete dilatation of the cervix so you can't apply the forks of probably and hence there will be a failed forks of or extensive laceration of the cervix. The presence of pelvic tumor which may obstruct the birth canal and then will cause failed forksips. Under fetal causes when we get a large head or hydrocephalic head this would cause failure of forks of delivery or extensive laceration of the birth canal.
And if the head is not in the proper position then application of the forks of the delivery will be difficult and hence failure of it. High head is already condemned and in high forks of delivery is not used anymore in present day practice. Then we have locked twins and double headed monsters as causes of failed forks of. Now when we come to discuss the complications that may occur in forks of delivery again we have maternal complications and fetal complications. Under maternal complications we get lacerations and injury or postpartum hemorrhage or terperecypces or even late complications as prolapse associated or not associated with stress incontinence or even habitual abortion
or any other type of incontinence. Under fetal complications we have injuries of different varieties of injuries or asphyxia of the baby. This is a wriggly forksips and it is used in low forks of delivery. It is a short, light, curved one designed to be used when the head is low down. Still it has got a pelvic curve and this is a pelvic curve and this is a cathartic curve and this is 11 inches in length. It also has got an English sliding lock. Here it is an English sliding lock and a short small handle.
Let us see together how we use it clinically. This is a case of delayed second stage while the head is low down on the perineum and we are going to use the wriggly forks in delivering the baby. As you can see here that is the hair of the baby here shown. It is a scalp. You can see how low down is the head. This is the wriggly forksips and then we should lock the wriggly forksips outside so we know how we are going to apply it. Here it is.
Then it has got two blades, right and left. We are going to apply the left blade which is held by the left hand and introduced onto the left side of the patient. We lubricate the blade and then we insert the right index and middle finger here between the head and the vagina. Then we smoothly insert the blade this way, sliding it inside. The same procedure will do it on the other blade, the right blade. We are holding the right blade with the right hand and is inserted onto the right side of the patient.
Again putting the fingers. Some people they put the four fingers either to intervene between the fetal head and the vagina. Here that is how to insert the blade and then it will be guided by the fingers inside and then we will smoothly insert it. When the forksips is probably inserted on the fetal head so it easily locks. Here easily locks. If there is any difficulty in locking the forksips take it out, re-examine the position of the fetal head and then apply the forksips again. Now we are going to do a small snip of a pisiotomy.
Here this is the midline. We are just on the right side of the midline, just a small snip. The patient here is under general anesthesia and that is why we didn't do infiltration of the perineum by a local anesthetic. Then gentle traction on the head. Again in the downward and backward direction. But here it doesn't require really much traction because the head is low down. It is not in the mid cavity as we have seen in the previous case. Here gently downwards, downwards here, downwards and backwards.
Again I am reminding you downwards and backwards in the direction of the birth canal. Then we support the perineum with a swab or a big piece of goose here. Supporting the perineum and then getting the head. Once the ox foot merges under the synapsis pubis, here then we lift the head up to get the suboxyptobregrammatic diameter extending the entritus here. And the baby is delivered by extension. Now the head is out and in this patient actually the baby was in the right occipital anterior position. We are going to help restitution of the head.
That's why I am turning it to the right side as it was, to the right side of the patient as it was. And then helping the external rotation to get the shoulders. This is a loop of the umbilical cord around the neck. So I am releasing the loop here. And then this is anterior shoulder is coming behind the synapsis pubis. Then the posterior shoulder and that is the rest of the baby here. As you can see that the back was on the right side of the patient.
Now the baby is out and then we like it the umbilical cord. We clamp it, cut it and then the baby is handed to pediatrician for resuscitation. This is Keelan's obstetric forksips. It still has two branches. Each has a blade, a shank, a lock of the sliding type and a handle. It is different from all other forksips by not having a pelvic calf. You can see how this forksip lies flat on the table. You see a very minimal pelvic calf compared to other obstetric forksips. Then we can see the difference.
Here it is. This is a regular forksip. And you see how the blades are elevated from the disc or the table. And here the Keelan's forksips are resting on the table. You can see the difference. That is the pelvic calf. Again this is Neville's forksips. You can see how the blades are elevated from the level of the table. Showing a marked pelvic calf. The idea of the regular forksips, not having a pelvic calf, that we can use it in acceptable stereo positions and then we can rotate the head all around in the pelvis
without reapplying the forksips. Only in one application used in rotation and delivery of the fetal head. And here this is a minimal, the advantage of having a minimal pelvic calf. And this is the indication, the main indication of using the Keelan's forksips. Here it has got two knobs on the handle. Here these two knobs are directed towards the baby's ox foot when applying the blades of the forksips. Here is a lock, a sliding type of lock. And this is the handle. The sliding lock allows the blades to slide up and down on each other
and correct acyclicism of the fetal head. We take the advantage of the Keelan's forksips not having a pelvic calf so we can apply it on the baby's head to rotate it and delivering it as well. And this particularly in persistent oxypetal posterior position in persistent mental posterior and in deep transverse arrest. It is not commonly used nowadays because Vintu's delivery has taken its place. Following the delivery of the baby, however instrumental or normal, you always check that the uterus is firmly contracted. And there is undue bleeding.
You first manage the case by compressing the uterus. In these cases you first check the uterus. If it is laced by normal compression, it should be done. This is of course accompanied by intravenous injection of the methargyne as well as syncynone. This photograph will show how we compress the uterus. The right hand is inside the vagina and the left hand is squeezing the uterus from the abdomen. The other picture is another maneuver in compressing the uterus. If the cervix, the degree of dilatation of the cervix allows the fist to go inside the uterine cavity
and with the left hand again on the patient's abdomen, we squeeze the uterus between both hands. You can maintain this maneuver for a few minutes until you feel the uterus is firmly contracted and no further bleeding is occurring. If still there is uterine bleeding, in spite the uterus is firmly contracted, the vagina and cervix must be explored. Let us see together how we are going to explore the vagina and the cervix. Here you can see how excessive vaginal bleeding is occurring. My left hand is on the uterus and the uterus is firmly contracted.
And then we are going to put a posterior vaginal speculum or sims speculum to see the cervix. And then with a sponge holding forksips, we are going to hold the anterior lip of the cervix. In this case, there should be about four or five sponge holding forksips available. We do not use the usual volcellum because the cervix after delivery is very soft and using the toothed volcellum would lacerate the cervix. That's why we use the sponge holding forksips, which is not traumatizing to the soft tissue of the cervix.
Here we are trying to catch the anterior lip as well as the posterior lip. We mop every now and then to see what we are holding with the sponge forksips. Now we can explore with the fingers now. And in this case, there is a tear on the right side of the cervix. Here it is, as you can see. That is a tear here. And then we are going to stitch the cervical tear. We're starting far back here at the angle of the tear, putting the needle through the posterior lip, then through the anterior lip.
And then this we usually use chromic cut-cut, number two chromic cut-cut to be strong. And then figure of eight hemostatic sutures, again through the posterior lip and then through the anterior lip of the cervix. That's the stitch. And then when we tie it, it would be a figure of eight. We'll make a figure of eight hemostatic sutures. Now this is a diagram to show what I'm doing. That's the anterior lip, posterior lip, and the needle through the, both of them, through the tear. Again to our patient, I'm tying here the first stitch.
And then we hold the tip on a artery forcipes. We don't cut the thread as my assistant wanted to do, but we hold it with an artery forcipes because it will help us traction. We can make traction on it so it exposes any further tear. So you can see this is another, the tear is further inside here. And then we are going to put another stitch proximal to the first one. You can notice that. Here it is. If you cut the thread of the first suture, you can't make good traction.
And this part would be slipped and you wouldn't notice it. But making a traction with an artery forcipes, holding the thread of the first suture, the angle of the tear can be exposed. And if it requires another stitch, you can put it as I'm doing now. Here it is, another stitch. Figure of eight hemostatic suture using chromic number two cat cut. On a round body needle, not using a cutting needle. Here this is another diagram to show what we are doing. That's the cervix and that's suture tear.
Now there are two stitches have been put and then the tear requires a third stitch. You can see and notice that the bleeding has stopped or even very minimal. Again with the round body needle, here through the posterior lip, through the anterior lip, another figure of eight suture. Here, back through the posterior lip and through the anterior lip of the cervix. You can see how the cervix is so soft after delivery. It is not the usual cervix which we see during vaginal examination, routine vaginal examination in non-pregnant patients.
The new tie, I usually put three knots actually on the tie to be safe and secure. One, two, here, three stitches have been put and then we knot and then here we are exposing now the tear which is being sutured and no bleeding has occurred. The bleeding has stopped. Then we cut the stitches and that's it. This is how to suture a cervical tear. Let us see together few instruments used in obstetric practice. This is mucus sucker and is used in sucking the mouth and nasopharynx of the baby after its delivery.
But nowadays we use a catheter, a soft catheter connected to a suction pump. It has got an opening on one end and then we suck on the other end and there is a reservoir in the middle. It is preferable to use the suction apparatus. This is Drus Meith catheter which is an S-shaped as you can see and it has got a curve which fits to the head of the baby. And it has got a here, this is a steel net which is threaded through its lumen and comes out at tip here.
And then when we apply it in the uterus and then to induce or to break the hind waters in cases where we cannot do forewater rupture as in high ballotable head. And then we introduce the Drus Meith and this curve will fit behind the baby's head here. It fits here and that part would be between the fetal head and the wall of the uterus. And then we push the steel net here like this and its tip will hit the amniotic sac, rupturing the amniotic sac here. And then the amniotic fluid will go, you can see the tip of the steel net here.
The amniotic fluid will pass through the hole and will come down through the other opening here. It has got a double exit. This is a picture to show the Drus Meith catheter inserted here between the baby's head and the wall of the uterus. Here, that's where it lies here. Here it is. And then by pushing the tip of the steel net we rupture the amniotic sac and the amniotic fluid is drippling. This is an external pelvic meter which is used in the past but not in present day practice.
As I have got two arms here where they move on a scale and is used to measure the bicepina diameter by fixing the two ends of the both arms. One on each side of the anterior superior spine. We can use it as well to measure the external conjugate by putting the two ends, one on the simpsons bupus and the other one at the back of the patient at the first sacral vertebra. And then we can read the distance between the two arms on the scale. This is a photograph which we use it as well in internal pilvimetry.
So these fingers are measuring the internal conjugate diameter through the vagina. And then we mark the length at the lower board of the simpsons bupus. And this then using the pilvimeter and assistant will measure the distance between the tip of the middle finger which was lying at the sacral pulmonary and the marked point which was lying under the simpsons bupus. And this will measure the internal conjugate diameter. By this we come to the end of this tape and hope to see you again in part to complete the anal obstetric procedures and operations.
Thank you and goodbye.
Transcript auto-generated from the video’s audio for accessibility and study. Educational content only — not medical advice.
Video Overview
From our Gynecology collection: Pelvic exams, Pap smears, IUD insertion, hysteroscopy and women's health procedures explained step by step. Browse all Gynecology videos →
SORT BY-
Top Comments
-
Latest comments