
- Physical Examination
- Surgical Examination
- Ophthalmology
- Clinical Skills
- Orthopedics
- Surgery Videos
- Laparoscopy
- Pediatrics
- Funny Videos
- Cardiothoracic Surgery
- Nursing Videos
- Plastic Surgery
- Otorhinolaryngology
- Histology and Histopathology
- Neurosurgery
- Dermatology
- Pediatric Surgery
- Urology
- Dentistry
- Oncology and Cancers
- Anatomy Videos
- Health and Fitness
- Radiology
- Anaesthesia
- Physical Therapy
- Pharmacology
- Interventional Radiology
- Cardiology
- Endocrinology
- Gynecology
- Emergency Medicine
- Psychiatry and Psychology
- Childbirth Videos
- General Medical Videos
- Nephrology
- Physiology
- Diet and Food Health
- Diabetes Mellitus
- Neurology
- Women Health
- Osteoporosis
- Gastroenterology
- Pulmonology
- Hematology
- Rheumatology
- Toxicology
- Nuclear Medicine
- Infectious Diseases
- Vascular Disease
- Reproductive Health
- Burns and Wound Healing
- Kidney Zone Podcast
- Other
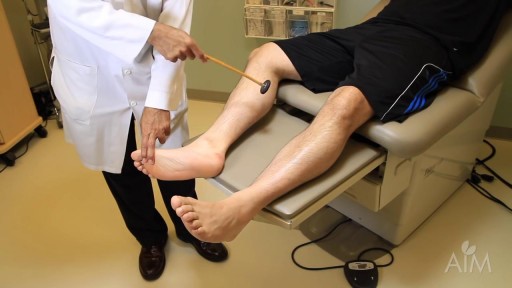
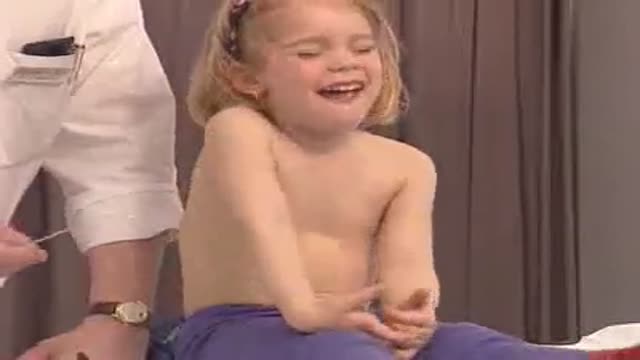


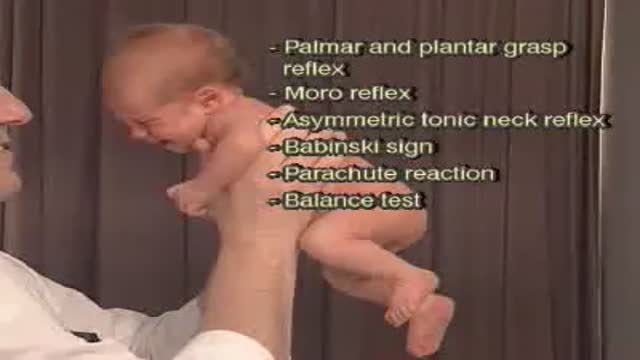

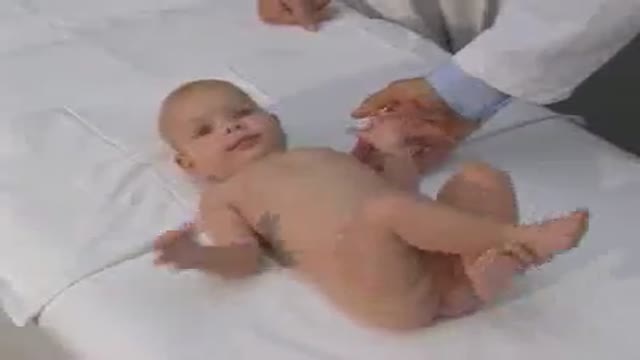












Deep tendon reflexes

Educational only: videos on MedicalVideos.com are for general information and are not medical advice. Always consult your own doctor about your health.
In a normal person, when a muscle tendon is tapped briskly, the muscle immediately contracts due to a two-neuron reflex arc involving the spinal or brainstem segment that innervates the muscle. The afferent neuron whose cell body lies in a dorsal root ganglion innervates the muscle or Golgi tendon organ associated with the muscles; the efferent neuron is an alpha motoneuron in the anterior horn of the cord. The cerebral cortex and a number of brainstem nuclei exert influence over the sensory input of the muscle spindles by means of the gamma motoneurons that are located in the anterior horn; these neurons supply a set of muscle fibers that control the length of the muscle spindle itself. Hyporeflexia is an absent or diminished response to tapping. It usually indicates a disease that involves one or more of the components of the two-neuron reflex arc itself. Hyperreflexia refers to hyperactive or repeating (clonic) reflexes. These usually indicate an interruption of corticospinal and other descending pathways that influence the reflex arc due to a suprasegmental lesion, that is, a lesion above the level of the spinal reflex pathways.
This video in 30 seconds
A teaching film shows how deep tendon reflexes and cerebellar function are tested in children. It covers the biceps, triceps, radial, patellar and Achilles reflexes with their spinal cord segments, the Jendrassik maneuver, and signs suggesting a pyramidal-tract lesion. Coordination is then assessed with finger-to-nose, heel-to-shin and rapid alternating movement tests, with notes on what is normal at each age.
Key points
- Five tendon reflexes are listed with their spinal cord segments
- A note for babies covers head position during reflex testing
- The Jendrassik maneuver is used when reflexes are hard to elicit
- Hyperactive reflexes and related signs are linked to pyramidal-tract lesions
- Coordination tests include finger-to-nose, heel-to-shin and rapid alternating movements
Chapters
- 0:05 — Tendon reflexes and cord segments
- 1:00 — Jendrassik maneuver for difficult reflexes
- 1:32 — Interpreting reflexes and lesion signs
- 1:51 — Cerebellar coordination testing begins
- 2:05 — Finger-to-nose and heel-to-shin tests
- 2:45 — Rapid alternating movements by age
Video Transcript
A teaching film on testing the deep tendon reflexes and cerebellar function in children, from the same pediatric examination series as the functional-integrity video. It covers the biceps, triceps, radial, patellar and Achilles reflexes with their spinal cord segments, the Jendrassik maneuver, the signs of a pyramidal-tract lesion, and coordination tests — finger-to-nose, heel-to-shin and rapid alternating movements — with notes on what is normal at each age.
Read the full transcript
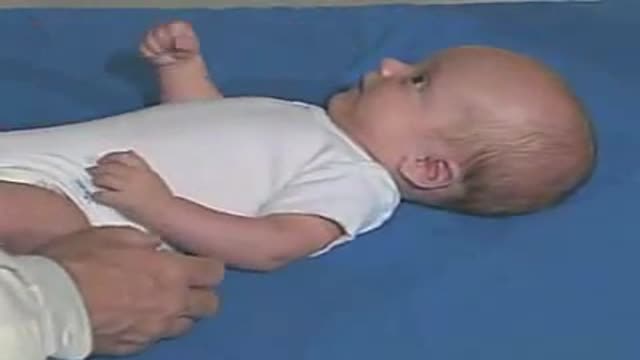
A routine part of the examination involves testing the biceps tendon reflex, corresponding to spinal cord segments C5 and C6. The triceps tendon reflex for segments C6 and C7, the radial reflex for segments C5 and C6, the patellar reflex for segments L2 to L4, and the Achilles reflex for segments S1 and S2. A particularity must be noted in babies. During the reflex test, the baby should look straight ahead because the asymmetric tonic neck reflex affects not only muscle tone, but reflexes as well. If the reflexes are difficult to trigger, we can facilitate eliciting them
with Gen Drasix maneuver in older children. Ask the patient to pull apart his fingers which are hooked together and elicit the reflex in that moment. In children, the deep tendon reflexes of the lower extremities are more lively than those of the upper ones, and the area where the reflex can be elicited is larger than with adults. The examination should determine whether the reflexes are present and symmetrical. Hyperactive reflexes may point to a lesion of the pyramidal track. The full picture of a pyramidal track lesion also comprises a positive Babinski sign,
spasticity, and sustained clonus. The function of the cerebellum is to coordinate the movements of individual muscle groups. The following tests are used to examine this. The finger-to-nose test can be used for children as young as three. Usually with its eyes closed, the child is asked to put its forefinger on its nose. Not all children cooperate equally well. This test shows possible defects such as a taxia or intention tremor. The corresponding test for the lower extremity is the heel-to-shin test. The child is asked to close her eyes and to slide her heel down along her shin.
Here too, both sides should be compared. A three-year-old child begins to imitate rapid alternating hand movements. At first the movement is slow and the elbows in the other hand are involved as well. Children do not achieve the skill that adults have until they are 10. In younger children, the degree of fine motor coordination can be assessed with the help of the Denver test appropriate for their age. Many things can also be observed if we simply allow the child to play. Older children, we assess coordination by assigning them skill tests,
such as buttoning and unbuttoning, or placing a cap onto a pen.
Transcript auto-generated from the video’s audio for accessibility and study. Educational content only — not medical advice.
Video Overview
From our Pediatrics collection: Pediatric videos: child health, newborn care, common childhood illnesses and pediatric procedures explained for parents, students and clinicians. Browse all Pediatrics videos →
Medical Videos
Free medical and surgery videos for patients, students and professionals — trusted since 2007.
Founded by Dr. Mohamed Ibrahim, MD, PhD — physician-scientist.
Follow us on Facebook · Instagram
SORT BY-
Top Comments
-
Latest comments