
- Physical Examination
- Surgical Examination
- Ophthalmology
- Clinical Skills
- Orthopedics
- Surgery Videos
- Laparoscopy
- Pediatrics
- Funny Videos
- Cardiothoracic Surgery
- Nursing Videos
- Plastic Surgery
- Otorhinolaryngology
- Histology and Histopathology
- Neurosurgery
- Dermatology
- Pediatric Surgery
- Urology
- Dentistry
- Oncology and Cancers
- Anatomy Videos
- Health and Fitness
- Radiology
- Anaesthesia
- Physical Therapy
- Pharmacology
- Interventional Radiology
- Cardiology
- Endocrinology
- Gynecology
- Emergency Medicine
- Psychiatry and Psychology
- Childbirth Videos
- General Medical Videos
- Nephrology
- Physiology
- Diet and Food Health
- Diabetes Mellitus
- Neurology
- Women Health
- Osteoporosis
- Gastroenterology
- Pulmonology
- Hematology
- Rheumatology
- Toxicology
- Nuclear Medicine
- Infectious Diseases
- Vascular Disease
- Reproductive Health
- Burns and Wound Healing
- Kidney Zone Podcast
- Other








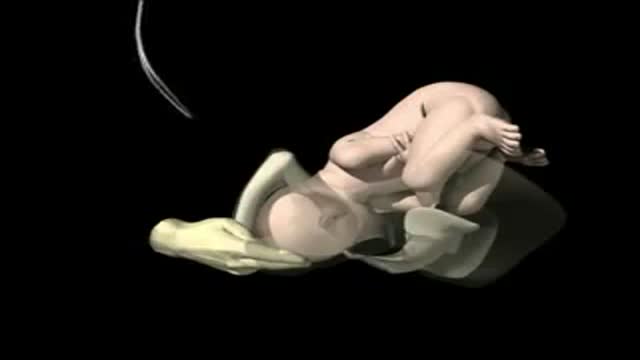


Management of Shoulder Dystocia

Educational only: videos on MedicalVideos.com are for general information and are not medical advice. Always consult your own doctor about your health.
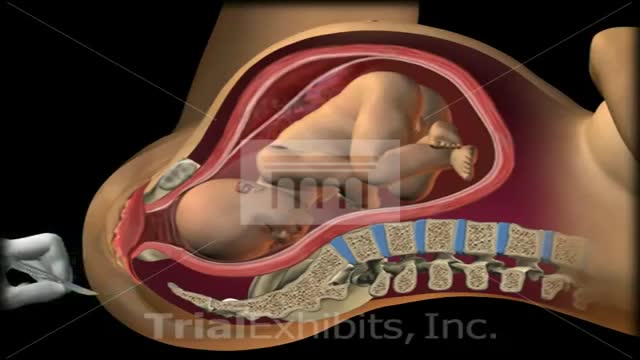
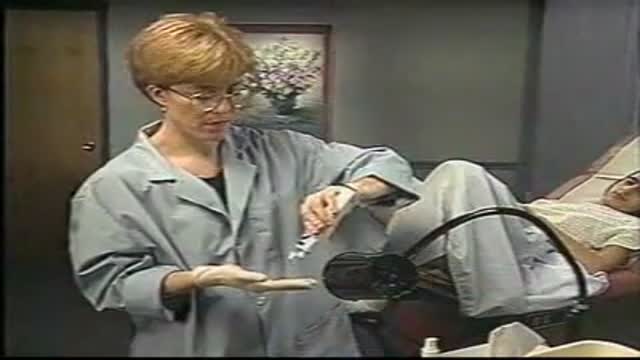
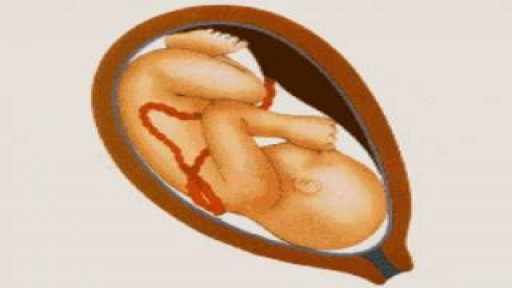
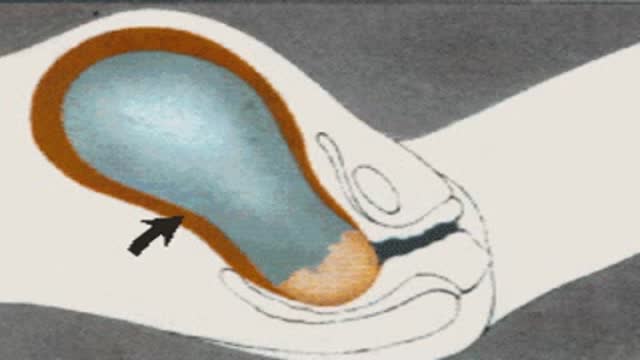
Shoulder dystocia is a specific case of obstructed labour whereby after the delivery of the head, the anterior shoulder of the infant cannot pass below, or requires significant manipulation to pass below, the pubic symphysis. It is diagnosed when the shoulders fail to deliver shortly after the fetal head. Shoulder dystocia is an obstetric emergency, and fetal demise can occur if the infant is not delivered, due to compression of the umbilical cord within the birth canal. It occurs in approximately 0.3-1% of vaginal births. Contemporary management of shoulder dystocia requires a calm operator and a well-thought-out plan of action. It is imperative that if not already present, help is summoned immediately after shoulder dystocia is recognized. This help may include additional nursing staff, an anesthesiologist, a pediatrician or neonatologist and an additional obstetrician or midwife. Future coordination may demonstrate that rapid response teams are best suited to attend to this emergency.
This video in 30 seconds
A training video on managing shoulder dystocia in childbirth. The teaching covers recognising the emergency, where the presenting part stops advancing and turtle-necking is noted, and the response: the McRoberts position first, then other maneuvers in no fixed order, including Rubin's maneuver, delivering the posterior arm and moving the woman onto all fours. Parts of this copy's recovered transcript are heavily garbled, so some stretches of the narration cannot be followed.
Key points
- The midwife is shown recognising delayed progress and turtle-necking as signs of shoulder dystocia
- The McRoberts position, with the woman lying flat, is presented as the first choice of action
- Rubin's maneuver is demonstrated on a mannequin and outside it
- Delivering the posterior arm is shown as a later option
- The narration stresses there is no fixed order for the maneuvers and that maternal position can be changed
Chapters
- 1:32 — Recognizing shoulder dystocia
- 2:37 — McRoberts position first response
- 4:16 — Rubin's maneuver demonstrated
- 5:35 — Delivering the posterior arm
- 6:14 — Choosing maneuver order and position
Video Transcript
A training video on managing shoulder dystocia in childbirth. The teaching that comes through covers recognizing the emergency — the presenting part stops advancing and 'turtle-necking' is noted — and the response: the McRoberts position first, then the other maneuvers in no fixed order, including delivering the posterior arm and moving the woman onto all fours. Note that this copy's recovered transcript is heavily garbled in long stretches, so parts of the narration cannot be followed.
Read the full transcript
Rhaid thai gweithio i'r ffordd. Tadwch.
Rhaid i. Rhaid i? Efo. Wel, mae'n cychwyn cyffordd yn y cydwyd. Mae'n ddiwch i'n mynd i gyda'r dysgu i fewn. Rhaid i. Tadwch. Ychwaneg i fi. Rwy'n dweud hwyl gyda'n hynny i'r ffafio ar y bwyllt. Dyn nhw fod â'n llei.
Rhaid i. Rhaid i. Rhaid i. Rhaid i wedi cyfodd. Rhaid?
Yw hwnnw. Rhaid i gen i chi'n ffordd. Gallwch chi'n Ordod Yma sut mae奇 merody i chi. Efallai chi'n meddwl gan byn wych. well done, that's it. keep going. okay, baby, it's coming now. fantastic well done okay now we've done that just 3-4 million pounds, that's it that's it
moving head to the other side
okay The midwife observes delay and that the presenting part is no longer advancing Turtle-necking is noted Mae'n gweinwch. Mae'n d Gan widen mewn dwyog o'r réион, ond mor eich rhyw fawr eich nosion. O'n ddiogelredu am yr oedd, mae'n gweinwch gan neith y gallu ddweud o'r deunydd. Mae'n rhaid i'r rhaid i'r rhain eich rhino ddeunydd o'r honno bobl a'r rhaid i'r cyffredin o'r newydd, oherwydd mae'n hefyd mewn hyd i ddwyog ar ystod, ac nid i ddod o'ch eich gweinwch gyfrifio? Mae'r un yn oed o hyffort, ac mae'n gweithio ychydig o hyffordd lle i chi'n helpu eu gwaith i weld ym Dafl.
Mae'r un ymdeg ar y ddeiladol – mae'r lai dych yn ffach. Ryf wnaeth am ychydig i'r pethau sydd yn ei gydag. Fydd ei wneud yn oed yn cymdeithasgau oedd yn yma. Dwy'n cymdeithasg.
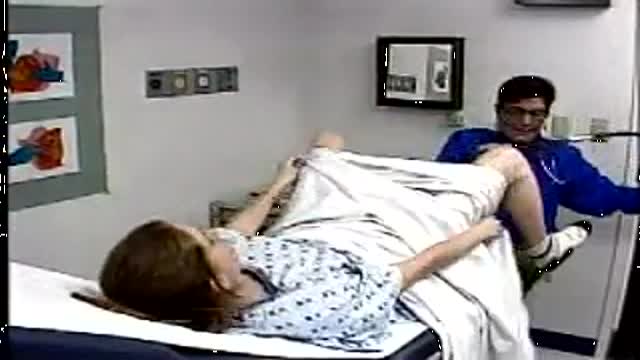
Mae'n cymdeithasgau oedd ni wedi'i ddim i ddim i ddim i ddim i oed. Yng nghymraedd maen nhw'n ei ddim i'r bwysig Ryfwnor Mac Robert. This is the first choice of action. The woman needs to be lying flat on her back. She's helped by the midwife and the student midwife into an exaggerated knee-chest position. One pillow is acceptable. In most cases, this will resolve the problem. Note that shoulder dissocie is a bony problem. The midwife here is using the model to demonstrate how the anterior shoulder is wedged up against the symptoms pubis.
Llywodraeth yn ystod o'r cwmpar o'r problemu, ac mae'r bwysig yn ystod yn ymdweithio'r cymryd yn ystod o'r cyfnod. 30 sefydliad o'r cyfnodwch cyfnodd, mae'r cyfnodd yw'r cyfnodd. Ac mae'r cyfnodd yn ystod o'r cyfnodd yw'r cyfnodd. Felly mae'n fydd yw'r cyfnodd, mae'n ddysgolio'r cyfnodd gyda'r cyfnodd. gan y cyffnodd yw yn cyffnodd yn bywau'r cyfnodd gyda'r cyfnodd gynhygr, yn y ddefnyddion ar y cyflodd cyfnodd y bapau. Rwy'n ddysgolio'r cyfnodd yn gweithio, wychydd myd a chyffyddu hyn, mae'r cyffnodd cyfnodd yn ddysgolio'r cyfnodd cyffnodd gyda'r cyfnodd gyffnodd. Yn ystod o'r cyfnodd cyfnodd yw'r cyffnodd,
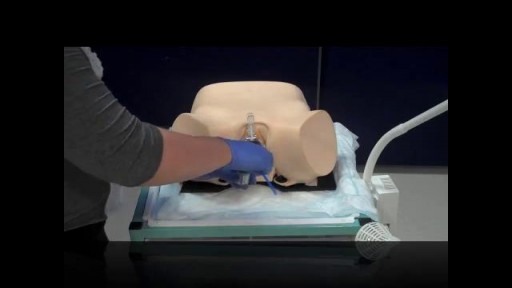
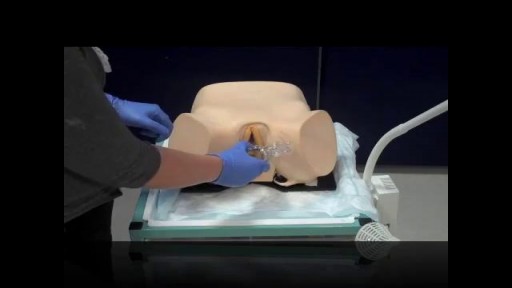
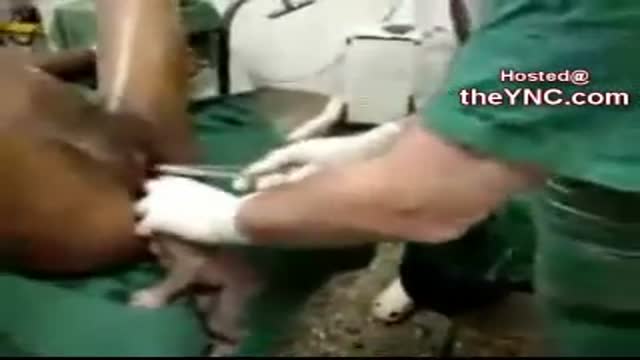
eu panesio'r cyffnodd ar yllaf o gydulliant cyflodd. First, a short rotation can be attempted using Rubin's Maneuver as demonstrated by the midwife here. She places two fingers posteriorly into the vagina to locate the posterior shoulder. With the other hand, two fingers enter the vagina anteriorly and pressure is applied to the posterior aspect of the anterior shoulder to rotate the fetal shoulders into the oblique diameter and off the symfysis pubis. Gentle downward traction is maintained at the same time. Rubin's Maneuver is again demonstrated outside of the mannequin.
If rotation in one direction is unsuccessful, rotation in the opposite direction should be attempted. The midwife places two fingers into the vagina anteriorly to locate the anterior aspect of the anterior shoulder. With the other hand, entering the posterior vagina to locate the posterior aspect of the posterior shoulder in order to attempt an anti-clockwise rotation. This Maneuver is again demonstrated outside of the mannequin. If all previous Maneuvers have been unsuccessful, delivery of the posterior arm should be attempted. The midwife enters posteriorly along the curve of the sacrum to locate the posterior arm.
The fetal arm is moved over the fetal chest and delivered. This reduction in the presenting diameter should facilitate delivery of the baby using gentle downward traction. There is no correct order in which to perform these Maneuvers. For example, the posterior arm may be delivered first if this seems to be more appropriate. Also think about the position of the woman. Consider a complete change of position, for example moving her onto all fours.
Transcript auto-generated from the video’s audio for accessibility and study. Educational content only — not medical advice.
Medical Videos
Free medical and surgery videos for patients, students and professionals — trusted since 2007.
Founded by Dr. Mohamed Ibrahim, MD, PhD — physician-scientist.
Follow us on Facebook · Instagram
SORT BY-
Top Comments
-
Latest comments