
- Physical Examination
- Surgical Examination
- Ophthalmology
- Clinical Skills
- Orthopedics
- Surgery Videos
- Laparoscopy
- Pediatrics
- Funny Videos
- Cardiothoracic Surgery
- Nursing Videos
- Plastic Surgery
- Otorhinolaryngology
- Histology and Histopathology
- Neurosurgery
- Dermatology
- Pediatric Surgery
- Urology
- Dentistry
- Oncology and Cancers
- Anatomy Videos
- Health and Fitness
- Radiology
- Anaesthesia
- Physical Therapy
- Pharmacology
- Interventional Radiology
- Cardiology
- Endocrinology
- Gynecology
- Emergency Medicine
- Psychiatry and Psychology
- Childbirth Videos
- General Medical Videos
- Nephrology
- Physiology
- Diet and Food Health
- Diabetes Mellitus
- Neurology
- Women Health
- Osteoporosis
- Gastroenterology
- Pulmonology
- Hematology
- Rheumatology
- Toxicology
- Nuclear Medicine
- Infectious Diseases
- Vascular Disease
- Reproductive Health
- Burns and Wound Healing
- Kidney Zone Podcast
- Other







Videoscopic Assisted Retroperitoneal Debridement for infected necrotizing pancreatitis

Educational only: videos on MedicalVideos.com are for general information and are not medical advice. Always consult your own doctor about your health.
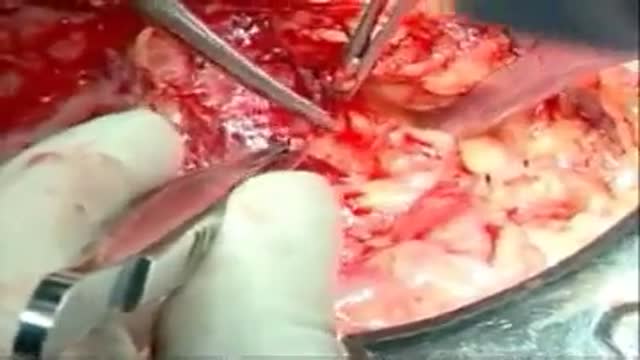
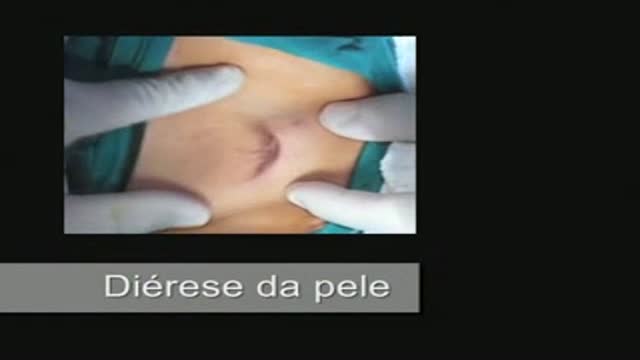
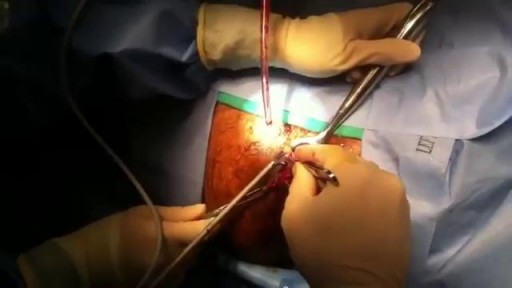
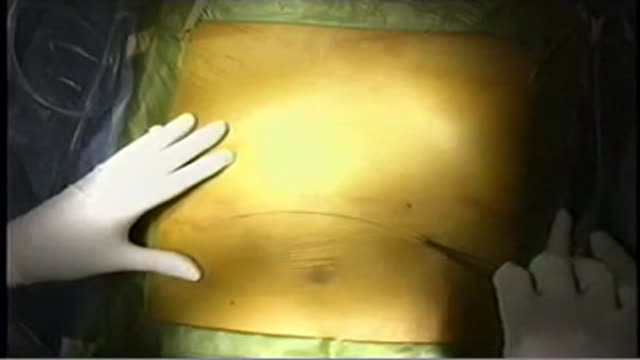
This is the CT of a 43 year old male patiënt with infected necrotizing pancreatitis that will undergo a VARD procedure; Videoscopic Assisted Retroperitoneal Debridment. Two weeks before this procedure two large bore percutaneous drains were placed in the peripancreatic collection. The patient i...s placed in supine position with the left side 30 degrees elevated. A 5-7 cm subcostal incision is made in the left flank. With help of CT images and by following the percutaneous drain, the subcutaneous tissue and the fascia are dissected and we enter the retroperitoneal peripancreatic collection. First, with a regular suction device any pus encountered is removed. Two long sympathectomy hooks are inserted in order to keep in the incision open. We than insert the zero degree laparoscope. The first necrosis encountered is removed under direct sight with the use of long grasping forceps. Following the percutaneous drain deeper into the cavity, parts of loosely adherent necrotic material are removed. Gently pulling we remove the necrotic tissue. The suction device is helpful in removing any fluid obstructing the view. Complete necrosectomy is not the ultimate aim of this procedure. Only loosely adherent pieces of necrosis are removed thereby keeping the risk of tearing underlying blood vessels to a minimum. In the rare case of extensive bleeding, the retroperitoneal cavity can be easily packed, either awaiting the bleeding to definitely stop or to act as a bridge to angiographic coiling. This patient is now 6 weeks after onset of disease. We always try to postpone surgical intervention, if possible up to 30 days. On the left side of the collection is the percutaneous drain. In this patient the drain had worked well for 2 weeks. When the patient deteriorated again it was decided to perform the VARD procedure. Large pieces of necrotic pancreas can be removed with VARD. This is a big advantage ov VARD over pure endosopic or percutaneous techniques. When all the necrotic tissue is removed we clean the cavity. Two drains are left in situ as a postoperative lavage system. The VARD procedure is performed via a 6 cm incision, which is closed and continuous postoperative lavage started immediately.
This video in 30 seconds
This video shows videoscopic assisted retroperitoneal debridement, known as VARD, for infected necrotizing pancreatitis in a 43-year-old man. Following previously placed percutaneous drains, the procedure is shown through a left flank incision, with a laparoscope and long grasping forceps used to remove loosely adherent necrotic material from the peripancreatic collection.
Key points
- Shows CT context for infected necrotizing pancreatitis before the VARD procedure
- Notes large-bore percutaneous drains were placed two weeks earlier
- Shows the left flank subcostal incision and entry into the retroperitoneal collection by following the drain
- Shows pus and necrotic material removed under laparoscopic view with grasping forceps
- Explains complete necrosectomy is not the aim; only loose necrotic material is removed
Video Transcript
This narrated operation shows a videoscopic-assisted retroperitoneal debridement (VARD) in a 43-year-old man with infected necrotising pancreatitis, performed about six weeks into his illness after percutaneous drains had been placed two weeks earlier. Through a small left-flank incision following the drain tract, the surgeons use a laparoscope and long forceps to remove only loosely adherent necrotic tissue, minimising the risk of tearing blood vessels, then leave drains in place for continuous postoperative lavage.
Read the full transcript
This is a 43 year old male with infected necrotizing pancreatitis that will undergo a physioscopic assisted retroparitoneal debrightment or a fart procedure. Two weeks before this procedure, two large bore percutaneous drains were placed in the peri-pancreatic collection. Here you see those two drains exit from the left flank and over the left pelvic rim. The patient is placed in a supine position with the left side 30 degrees elevated. A 5 to 7 centimeter subcostal incision is made in the left flank. With help of the CT images and by following the percutaneous drain, the subcutaneous tissues
and the fascia are dissected and we enter the retroparitoneal peri-pancreatic collection. The patient is placed with a regular suction device and the pus encountered is removed and then two long simpatectomy hooks are inserted in order to keep the incision open. We then insert a regular 0 degree elliposcope and remove the first necrosis encountered on the direct side with the use of long grasping forceps. Having the percutaneous drain deeper into the cavity, parts of loosely adherence necrotic material are removed. Gently pulling, we remove the necrotic tissue. The suction device may be helpful in removing any fluid obstructing the view.
Completely cosectomy is not the ultimate aim of this procedure. Only loosely adherent pieces of necrosis are removed, thereby keeping the risk of tearing underlying blood vessels to a minimum. In the rare case of extensive bleeding, the retroparitoneal cavity can be easily packed, either waiting the bleeding to definitely stop or to act as a bridge to angiographic coiling. This patient is now six weeks after onset of disease. We always try to postpone surgical intervention, if possible up to 30 days. On the left side of the collection you can see the percutaneous drain.
This patient worked well for two weeks, but when the patient deteriorated again, it was decided to perform the farce procedure. A big advantage of fart over pure endoscopic transgastic or percutaneous techniques is that with fart it is possible to remove big chunks of necrotic material via the incision. Here you see such a large chunk of necrotic pancreas being removed. With the leproscopic tools we can see which parts of the necrosis are loosely adherent. If we find them, those pieces are removed. So the surgeon is holding the leproscope in his left hand and a regular rinsing device
in his right hand. When all the necrotic material is removed, we clean out the cavity. On the endoscopic image you can see the two drains in the cavity. After the incision is closed, these drains are left inside too and act as a continuous post-operative lavage system. We increase the lavage fluid up to 10 liters of saline per 24 hours.
In this case we use a low pressure pulse lavage system and the end of the operation to remove the last chunks of necrosis and pus. This was the necrosis removed during the procedure. The fart was performed via a 6 cm incision which was closed and continuous post-operative lavage started immediately.
Transcript auto-generated from the video’s audio for accessibility and study. Educational content only — not medical advice.
Video Overview
From our Surgery Videos collection: Surgery videos: watch real operations step by step — general, laparoscopic and specialist surgery performed in the OR, explained for students and surgeons. Browse all Surgery Videos videos →
Medical Videos
Free medical and surgery videos for patients, students and professionals — trusted since 2007.
Founded by Dr. Mohamed Ibrahim, MD, PhD — physician-scientist.
Follow us on Facebook · Instagram
SORT BY-
Top Comments
-
Latest comments